
Real-World Data in Healthcare Technology Incorporation: A Strategic Opportunity for Latin America
Marcos Santos, MD, PhD, ISPOR Brazil Chapter; Alfonso Gutierrez-Aguado, MD, PhD, Rosina Hinojosa, MSc, MPH, ISPOR Peru Chapter; Daniela Paredes-Fernandez, MPH, ISPOR Chile Chapter; Maria Gabriela Fernandez, PharmD, MBA, Graciela Luraschi, PharmD, MBA, Bruno Boietti, MD, María Luisa da Silva Soca, MSc, ISPOR Argentina Chapter; Juan Guillermo Barrientos G, MD, MSc, ISPOR Colombia Chapter; Rodrigo DeAntonio MD, MSc, DrPH, ISPOR Central America and the Caribbean Chapter
From Rhetoric to Decisional Use
Real-world data (RWD) and real-world evidence (RWE) are now occupying an increasingly structured space in health technology assessment (HTA) frameworks in high-income countries. In Latin America, the discussion has imported this technical vocabulary, but without questioning the local conditions that determine what type of RWD can really underpin coverage and incorporation decisions. The pertinent question, especially for a Latin American audience, is: When does RWE really contribute to a better coverage decision, and when does it function merely as a methodological ornament accompanying a file without substantially modifying the inference that sustains the recommendation?
The consolidation of the HARPER (HARmonized Protocol Template to Enhance Reproducibility) framework published by the joint ISPE/ISPOR working group and the expansion of initiatives such as RCT DUPLICATE showed that observational studies can, under well-defined conditions, produce effect estimates comparable to those of randomized trials—but also that these conditions are demanding and often not met. Adoption of the RWE discourse without careful appropriation of its methodological standards represents a tangible risk: decisions supported by apparently empirical, but methodologically fragile, evidence.
This article proposes a shift: to stop understanding RWE as an economic substitute for randomized clinical trials and to recognize it as a complementary instrument, with its own questions and demanding methodological standards.
Answering Questions That Matter Most
What interests the payer is not that evidence is “real-world,” but that the estimate of its effect is causal. Hernán and Robins put it precisely: any observational analysis that pursues a causal conclusion is, implicitly, an attempt to emulate an objective trial (or target trial). The key factor is whether this emulation is explicit—and therefore criticizable, replicable, calibratable—or whether it is implicit in the form of an opaque statistical model.
The RCT DUPLICATE program, led by Schneeweiss and Franklin, provides a concrete empirical basis for assessing the scope of RWE. In the first 10 prospectively planned emulations of cardiovascular trials of antidiabetic and antiplatelet drugs, RWE replicated the regulatory conclusion of the RCT in 6 out of 10 cases, and the hazard ratio fell within the 95% confidence interval of the corresponding RCT in 8 out of 10. Subsequent results, from a total of 32 emulations, concluded that the agreement between RWE and RCTs depends critically on the choice of active comparators, the quality of the outcome measurement, and the ability of the database to capture clinically relevant confounding variables.
RWE does not replace the RCT; it answers questions that the RCT structurally cannot answer—or will not answer—for reasons of cost, ethical feasibility, or lack of commercial incentives. Among these questions are precisely those that matter most to the Latin American payer: effectiveness in populations with comorbidities excluded from the pivotal trials, real patterns of adherence and therapeutic persistence, use of health resources associated with incorporation, and performance of technology in subpopulations defined by access, geography, or socioeconomic level.
Adoption of real-world evidence discourse without careful appropriation of its methodological standards represents a tangible risk: decisions supported by apparently empirical, but methodologically fragile, evidence.
Minimum Requirements
Recent methodological literature—from HARPER to the NICE guidelines on RWE in HTA and the discussion of target trial emulation in the Methods Explained column of Value & Outcomes Spotlight—converges on 3 minimum requirements for RWE: prespecified protocol recorded before seeing the results; transparent description of the origin and quality of the data; and rigorous application of causal inference methods to control confounding, including sensitivity and unobserved bias analyses.
In the absence of these conditions, what is produced is not RWE but something less: a descriptive analysis with causal claim. This distinction is critical in the regulatory context, because the confusion between the 2 registries—analytical and causal—is what allows studies of low methodological quality to circulate as “real-world evidence” in records of HTA agencies. The problem is not the absence of data; it is the absence of quality control and analytical governance.
What is it about Latin America that makes RWE more necessary than in other contexts but also more difficult to produce? Key contributing factors include the fragmentation of Latin American health systems, the scarcity of interoperable records, and the increasing budgetary pressure on payers.
The Illusion of Abundant Data
Latin American populations are underrepresented in the pivotal clinical trials that inform regulatory approvals and, subsequently, incorporation recommendations. The differences between Latin American populations and those in the global north—related to prevalence of comorbidities, genetic profile, access to timely diagnosis, and continuity of care—make the direct extrapolation of effectiveness estimates informed approach at best. In this context, RWE is not a methodological luxury; it is a natural mechanism to bridge the gap between imported evidence and local performance.
One of the most lucid observations of the regional panorama—formulated during an RWE session of ISPOR Latin America 2021—is that the Latin American problem is not the scarcity of data, but the shortage of analytical capacity and data governance.
Brazil generates massive volumes of information through DATASUS, the information systems of the Agência Nacional de Saúde Suplementar (ANS) and the electronic registries of operators and hospitals. Mexico has Sistema Nacional de Información en Salud (SINAIS); Colombia with its insurance records; Argentina with heterogeneous national and provincial bases, highly fragmented and with limited interoperability. [See Appendix 1 for a country-by-country overview of RWE data sources and institutionality.]
What is missing is not information; we lack the following: a way to make this information cumulative, unique identification of the patient through the cycle of care, validated algorithms for phenotyping conditions in administrative codes, and above all, a critical mass of analysts trained in computational epidemiology.
This observation has an uncomfortable practical consequence: The mere existence of large databases does not produce useful RWE. On the contrary, it may produce descriptive studies with the appearance of comparative analysis, whose uncritical inclusion in the regulatory and coverage ecosystem can deteriorate—not improve—decision-making quality. This, in turn, will negatively impact the credibility of the RWE.
In our reality, where the per capita health budget is a fraction of the European one, real-world evidence emerges as the only feasible way to generate local comparative evidence in many categories.
The Budget Question
Here we come to the most relevant angle for Latin American payers, public and private. Pragmatic RCTs and adaptive platforms are expensive even in high-income systems; in our reality, where the per capita health budget is a fraction of the European one and the capacity to cofinance local confirmatory studies is limited, RWE emerges as the only feasible way to generate local comparative evidence in many therapeutic categories. This is particularly true for high-cost drugs and advanced therapies, where incorporation is decided based on evidence from a single pivotal trial and where the space for risk-sharing contracts and managed entry agreements depends, crucially, on the payer’s ability to monitor outcomes in its own population.
RWE makes it possible to take advantage of existing data in administrative systems, clinical records, and electronic records, significantly reducing costs and time for producing evidence compared with conventional experimental studies. This difference is not trivial from the payer’s perspective: In systems where every dollar invested in evidence generation competes directly with the effective coverage of benefits, RWE is the only feasible alternative for producing local comparative information in multiple therapeutic areas.
It is important, however, to understand that while RWE is cheaper than a new RCT, it is not cheap. An interoperable, governed, auditable data infrastructure with permanent analytical capacity requires sustained investment in the medium term. Latin American health systems have historically shown difficulty in sustaining such investments because there are always more urgent problems. Ultimately, the decision to build RWE’s capacity competes, at the margins, with the decision to incorporate the next technology.
Another important condition, which the regional debate tends to underestimate, is that the existence of data is not equivalent to the capacity to produce evidence. In most Latin American countries, a significant proportion of the relevant information is generated in insurance schemes, particularly in populations covered by social security or public insurance, where there are continuous records of use, prescription, and clinical outcomes. However, these datasets often remain underutilized due to limitations in interoperability, standardization, and analytical capability. In this sense, the greatest limitation is not the absence of information, but the absence of institutional structures that allow the transformation of administrative claims data into valid causal inferences and inputs for coverage decisions.
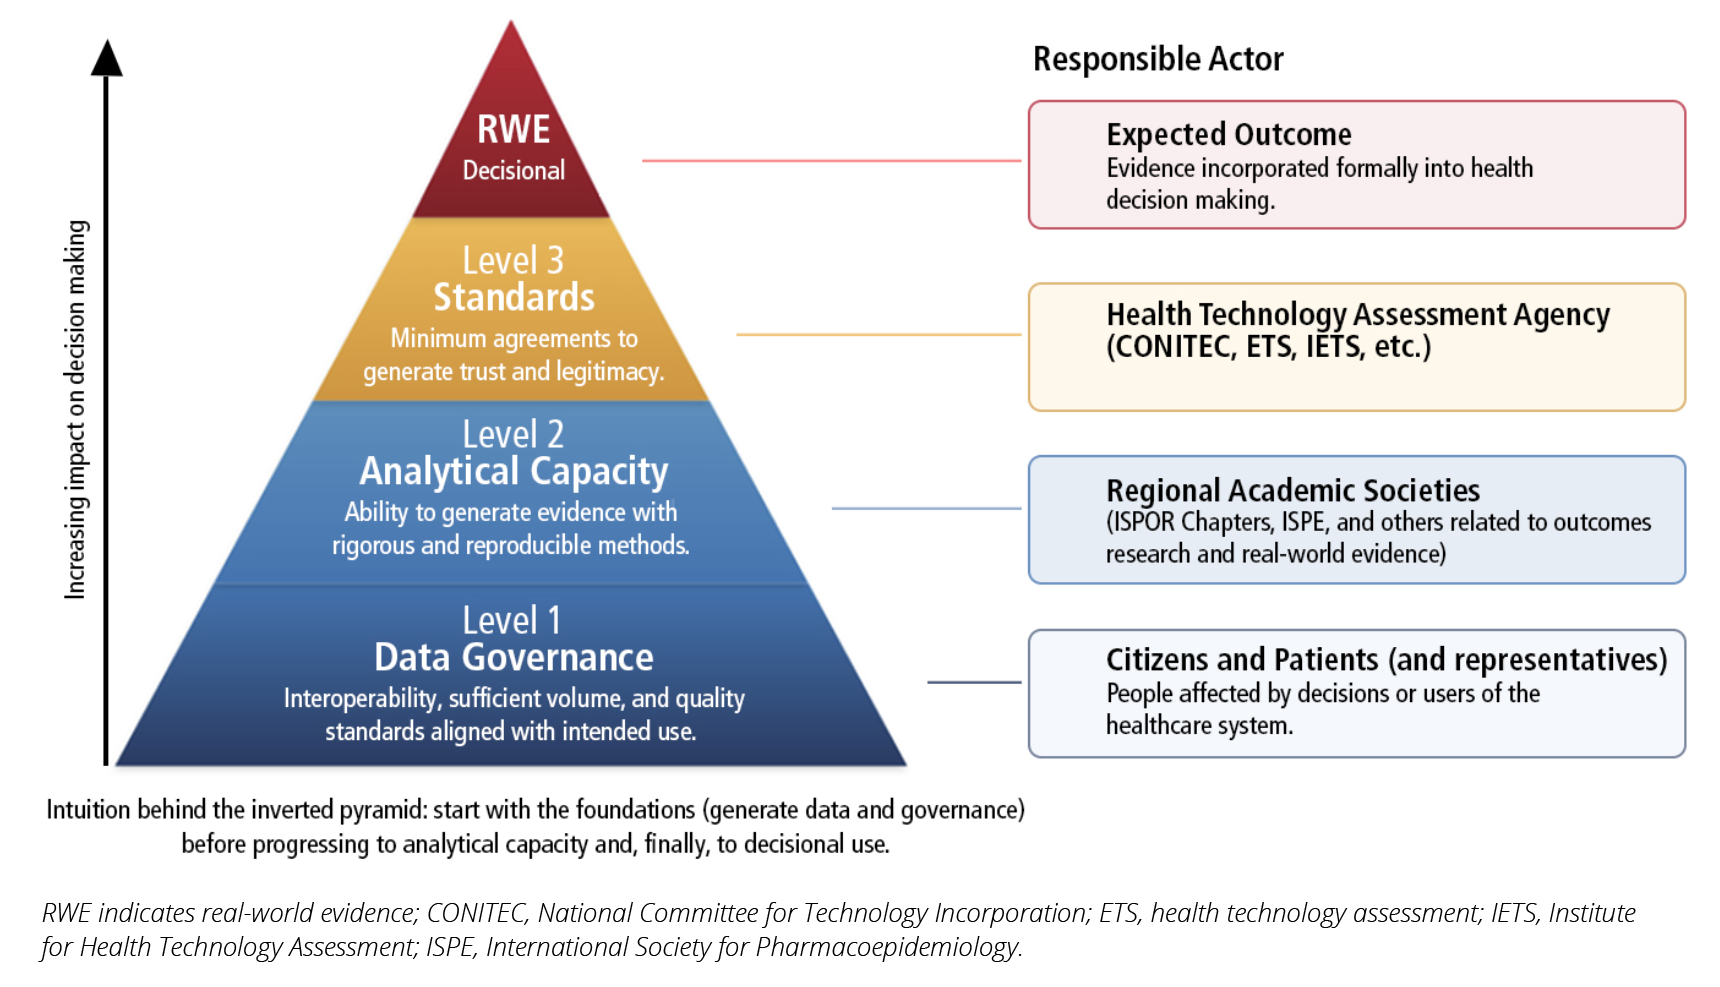
RWE’s agenda in Latin America, therefore, cannot be reduced to database expansion, but requires a deliberate investment in analytical capabilities, epidemiology and artificial intelligence tools, causal design, and algorithm validation, to allow the economic advantage of RWE to be effectively translated into more informed decisions (Figure 1).
Without this transition, beyond the risk of producing lower quality evidence, the region risks continuing to generate large volumes of data without converting it into useful knowledge for financial sustainability and health technology management.
Figure 1. Minimum agenda for a decisional RWE in Latin America
Systemic Fragmentation
Latin American systems are pluralistic and fragmented. This creates a serious counterfactual problem for RWE: the observable population in a database rarely represents the population on which the coverage decision will be made, and adjustment algorithms designed for homogeneous databases (such as those in the United States or England) do not translate directly. They are therefore of no use here. [See Appendix 2 for a country-by-country breakdown.]
As a hypothetical example, a comparative effectiveness study on the use of any medication, constructed with data from a Brazilian supplementary health operator of class A/B, will produce a perfectly valid estimate—for that population. Extrapolating it to the Unified Health System (SUS) population, with a different epidemiological profile, adherence, and comorbidities, requires transportability assumptions that are rarely made explicit in the files submitted to CONITEC. Even more than RWE produced in integrated systems, RWE in Latin America needs a rigorous discussion on intracountry external validity.
Real-world evidence in Latin America is not only a methodological complement to the clinical trial, but a structural response to simultaneous conditions of budgetary constraint, systemic fragmentation, and underutilization of data generated in insured populations.
A Minimum Agenda for Change
At this point, some urgent priorities can be deduced.
- Regional HTA agencies should formally adopt reporting standards for HARPER-aligned or equivalent RWE studies, and base conditional acceptance of this type of evidence on pre-registered protocols.
- Payers—both public and supplemental health—should invest in interoperable data infrastructure rather than ad hoc analytics. The natural succession between data governance and analytical capacity cannot be reversed.
- Regional academic societies, including the Latin American Chapter of ISPOR, have a clear role in the formation of human capital capable of producing and critiquing RWE with international standards. This is, perhaps, the most restrictive bottleneck in the medium term.
In these contexts, RWE emerges not only as a methodological complement to the clinical trial, but as a structural response to simultaneous conditions of budgetary constraint, systemic fragmentation, and underutilization of data generated in insured populations.
The central challenge is not whether the region should adopt RWE, but whether it can do so under conditions that allow the construction of valid counterfactuals, guarantee external validity, and sustain minimum standards of causal inference in systems characterized by heterogeneous care trajectories and noncomparable databases. Investment in interoperability, standardization, and analytical capacity is necessary for the economic advantage of RWE to be translated into more efficient decisions.
RWE will not, on its own, solve the prioritization dilemmas faced by Latin American systems. But it can, if taken seriously, shift part of the incorporation debate from the realm of extrapolation to that of observed local performance.
